

International Journal of Orthopaedics Research(IJOR)
ISSN: 2690-9189 | DOI: 10.33140/IJOR

Impact Factor: 1.6

Research Article - (2026) Volume 9, Issue 3
Comparative Efficacy and Safety of Platelet-Rich Plasma Alone Versus Platelet-Rich Plasma Combined with Hyaluronic Acid for Knee Osteoarthritis: A Systematic Review
 , Thiago Cavalcante Ribeiro , Douglas de Melo Moura , Gabriel de Castro Monteiro , Helena Maria Mendes Marques , Gabriel Ricardo de Araújo Ruivo , Edward Rodrigues De Oliveira Filho , Frederico Tannus de Almeida , Sylvane Fernandes Santos Oliveira and Karollyne da Silva Morais
Received Date: Aug 10, 2026 / Accepted Date: Sep 14, 2026 / Published Date: Sep 22, 2026
Copyright: ©2026 Eric Lorenzeto Cardoso, et al. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited
Citation: Cardoso, E. L., Ribeiro, T. C., Moura, D. D. M., Monteiro, G. D. C., Marques, H. M. M., et al. (2026). Comparative Efficacy and Safety of Platelet-Rich Plasma Alone Versus Platelet-Rich Plasma Combined with Hyaluronic Acid for Knee Osteoarthritis: A Systematic Review. Int J Ortho Res, 9(3), 01-12.
Abstract
Background: Knee osteoarthritis is a prevalent degenerative joint disease characterized by pain, stiffness, functional limitation, and progressive impairment in quality of life. Intra-articular platelet-rich plasma (PRP) and hyaluronic acid (HA) are widely used conservative injectable therapies, and their combination has been proposed to integrate the biological effects of platelet-derived mediators with the viscoelastic and lubricating properties of HA.
Objective: This systematic review aimed to evaluate the efficacy and safety of PRP alone compared with PRP combined with HA in patients with knee osteoarthritis, considering pain, physical function, stiffness, patient-reported outcomes, adverse events, and follow-up duration across available clinical studies.
Methods: Clinical studies published in English between 2011 and 2026 were reviewed. Eligible studies included randomized controlled trials, prospective clinical studies, retrospective comparative studies, and experimental clinical studies evaluating PRP alone, HA alone, PRP+HA, or related injectable comparators in knee osteoarthritis. The main outcomes were pain, physical function, stiffness, quality of life, treatment response, adverse events, and methodological quality. Because of heterogeneity in study design, PRP preparation, HA formulation, injection protocol, comparator groups, and follow-up duration, the findings were synthesized qualitatively.
Results: Twenty-five clinical studies were included. PRP-based interventions were consistently associated with improvement in pain and physical function, with a favorable safety profile. PRP alone was frequently superior to HA, particularly at medium- and long-term follow-up, although this finding was not uniform across all studies. Studies comparing PRP+HA with HA alone generally favored the combined intervention, suggesting that the addition of PRP may enhance the clinical effect of viscosupplementation. However, direct comparisons between PRP+HA and PRP alone showed heterogeneous results, with no consistent evidence that the combined treatment is superior to PRP monotherapy. Most adverse events were mild and transient, including post-injection pain, swelling, stiffness, or local discomfort.
Conclusion: PRP-based intra-articular therapy appears to be effective and safe for symptomatic knee osteoarthritis. PRP+HA may offer clinical advantages over HA alone, but its superiority over PRP alone remains uncertain. Therefore, PRP+HA should be interpreted as a promising combined approach rather than a definitively superior alternative to PRP monotherapy.
Keywords
Platelet-Rich Plasma, Hyaluronic Acid, Knee Osteoarthritis, Intra-Articular Injection, Viscosupplementation
Introduction
Knee osteoarthritis (KOA) is a chronic degenerative joint disorder characterized by progressive articular cartilage breakdown, osteophyte formation, subchondral sclerosis, synovial changes, pain, stiffness, effusion, and progressive limitation of daily activities. It is one of the most prevalent musculoskeletal causes of disability and reduced quality of life, particularly in older adults and women. Because no curative disease-modifying treatment is currently established for most patients, clinical management remains primarily symptomatic, aiming to relieve pain, improve function, reduce disability, and delay surgical intervention when possible [1,2].
Conservative management of KOA includes weight control, therapeutic exercise, physical therapy, oral analgesics, nonsteroidal anti-inflammatory drugs, corticosteroid injections, viscosupplementation with hyaluronic acid (HA), and biologic intra-articular therapies such as platelet-rich plasma (PRP). HA is a glycosaminoglycan naturally present in synovial fluid and connective tissues. In osteoarthritic joints, the concentration and molecular weight of endogenous HA decline, reducing the viscoelastic and lubricating properties of synovial fluid. Exogenous HA is therefore used to restore joint lubrication, attenuate synovial inflammation, reduce nociceptive stimulation, protect cartilage, and potentially promote endogenous HA synthesis [1,3].
PRP is an autologous blood-derived product obtained through centrifugation, resulting in a platelet concentrate enriched with growth factors, cytokines, and plasma proteins. Its proposed mechanisms in KOA include modulation of inflammation, stimulation of chondrocyte and synoviocyte activity, promotion of cartilage matrix homeostasis, regulation of angiogenesis, and enhancement of endogenous HA synthesis. Several clinical trials and meta-analyses have reported that PRP may provide superior pain and functional outcomes compared with HA alone in selected patients with mild-to-moderate KOA; however, heterogeneity in PRP preparation, leukocyte content, platelet concentration, activation method, injection volume, and treatment schedule complicate interpretation of the evidence [3,4].
The combined use of PRP and HA has been proposed because the two agents may exert complementary biological and biomechanical effects. HA may improve joint lubrication and support growth factor diffusion, whereas PRP may provide anabolic and anti-inflammatory mediators that target the degenerative joint microenvironment. Experimental and clinical data suggest that HA may increase the release or persistence of PRP-derived growth factors and that combined therapy may influence inflammatory cytokines and cartilage-related pathways. Nevertheless, whether this combination produces a true synergistic clinical effect remains uncertain [1,5].
Clinical studies directly comparing PRP alone with PRP combined with HA have produced inconsistent findings. Some randomized trials have reported greater improvements in WOMAC pain, stiffness, function, static balance, or short- to medium-term symptom relief after combined PRP-HA protocols compared with PRP alone [3,6,7]. Conversely, other trials have found no clinically relevant superiority of adding HA to PRP, including evidence showing similar outcomes between PRP monotherapy and concomitant PRP-HA therapy up to 24 months [8]. These discrepancies may reflect differences in study design, disease severity, HA molecular weight, timing of administration, number of injections, PRP formulation, follow-up duration, and outcome measures.
Given the increasing clinical use of intra-articular biologic and viscosupplementation strategies, a rigorous synthesis of the available clinical evidence is required. Therefore, the objective of this systematic review is to evaluate the efficacy and safety of platelet-rich plasma alone compared with platelet-rich plasma combined with hyaluronic acid in patients with knee osteoarthritis, considering pain, physical function, stiffness, patient-reported outcomes, adverse events, and follow-up duration across available clinical studies.
Methods
Study Design and Reporting Framework
This systematic review was conducted to synthesize clinical evidence regarding the use of intra-articular platelet-rich plasma (PRP), either as an isolated intervention or in combination with hyaluronic acid (HA), for the treatment of knee osteoarthritis. The methodological structure followed the recommendations of the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 statement, with predefined procedures for formulation of the research question, identification of studies, eligibility assessment, data extraction, methodological quality appraisal, and qualitative synthesis of the evidence
Research Question and PICO Strategy
The review was guided by the following research question: in adult patients with knee osteoarthritis, does intra-articular PRP combined with HA provide superior clinical outcomes when compared with PRP alone or other injectable comparators? The population consisted of adults with clinical and/or radiographic diagnosis of knee osteoarthritis. The intervention of interest was intra-articular PRP associated with HA, administered either simultaneously or sequentially. The main comparator was PRP alone; however, studies including HA alone, corticosteroid, ozone, saline, placebo, or other injectable biologic therapies were also considered when they contributed clinically relevant comparative evidence. The outcomes of interest included pain, stiffness, physical function, patient-reported outcome measures, quality of life, treatment satisfaction, analgesic consumption, adverse events, and follow-up duration.
Information Sources
The literature search was performed in PubMed/MEDLINE, Scopus, Web of Science, Embase, Cochrane CENTRAL, PEDro, SciELO, and Google Scholar. Manual research was also performed in the reference lists of eligible studies to identify additional clinical articles that could meet the inclusion criteria. The search included studies published from January 2011 to May 2026. Only articles published in English and available as free full text were considered eligible for inclusion.
Search Strategy and Boolean Descriptors
The search strategy combined controlled vocabulary and free-text terms related to platelet-rich plasma, hyaluronic acid, and knee osteoarthritis. The main Boolean expression used was: (“platelet-rich plasma” OR PRP OR “plasma rich in growth factors” OR PRGF OR “autologous conditioned plasma”) AND (“hyaluronic acid” OR hyaluronan OR viscosupplementation OR “sodium hyaluronate”) AND (“knee osteoarthritis” OR “knee OA” OR gonarthrosis OR “degenerative knee disease”). To identify studies specifically evaluating combined therapy, the following expression was also applied: (“platelet-rich plasma” OR PRP) AND (“hyaluronic acid” OR HA OR hyaluronan) AND (combined OR combination OR concomitant OR sequential OR “one-week prior”) AND knee AND osteoarthritis. A clinical-study filter was added when supported by the database: (“clinical trial” OR randomized OR randomised OR “randomized controlled trial” OR “controlled trial” OR prospective OR retrospective OR experimental) AND (PRP OR “platelet-rich plasma”) AND (HA OR “hyaluronic acid”) AND knee. Outcome-oriented terms were also used to improve sensitivity, including WOMAC, KOOS, VAS, IKDC, Lequesne, pain, stiffness, function, and adverse events.
Eligibility Criteria
Studies were included when they met all predefined eligibility criteria. Eligible articles had to be clinical studies in humans, include adult participants diagnosed with knee osteoarthritis, evaluate intra-articular PRP, HA, PRP combined with HA, or another directly comparable injectable intervention, and report at least one clinical outcome related to pain, function, stiffness, quality of life, treatment response, or safety. Randomized clinical trials controlled clinical trials, prospective clinical studies, retrospective comparative clinical studies, and experimental clinical studies were accepted. Review articles, systematic reviews, meta-analyses, editorials, letters without original data, protocols without results, animal studies, in vitro investigations, surgical-only studies, non-English articles, inaccessible full texts, and studies without extractable clinical outcome data were excluded.
Study Selection
All retrieved records were exported to a reference-management system, and duplicate references were removed before the screening phase. Titles and abstracts were then independently assessed according to the predefined eligibility criteria. Studies considered potentially relevant were retrieved and evaluated in full text to confirm their inclusion. The selection process primarily prioritized clinical studies directly comparing platelet-rich plasma (PRP) alone with PRP combined with hyaluronic acid (HA). However, considering the limited number of direct comparative studies available, additional clinical investigations comparing PRP with HA or PRP+HA with HA were included as complementary evidence when they addressed the same clinical condition, used intra-articular administration, and reported comparable clinical outcomes.
The study selection process is summarized in Figure 1. Initially, 832 records were identified through database searching. After duplicate removal, 545 records remained for title and abstract screening. Of these, 419 records were excluded because they did not meet the eligibility criteria. Subsequently, 126 full-text articles were assessed for eligibility, and 101 articles were excluded for the following reasons: review or meta-analysis design, non-clinical study design, absence of a PRP/HA comparator, non-English language or unavailable free full text, duplicated population, or insufficient clinical data. After the complete screening and eligibility process, 25 clinical studies were included in the qualitative synthesis and quantitative synthesis considered when the data were sufficiently homogeneous.

Figure 1: PRISMA flow diagram of study selection
Data Extraction
Data was extracted using a standardized form developed for this review. The extracted variables included author, year of publication, country, study design, sample size, demographic characteristics, diagnostic criteria, Kellgren-Lawrence grade when available, intervention arms, comparator groups, PRP preparation method, leukocyte content when reported, HA formulation and molecular weight when available, number of injections, injection interval, use of imaging guidance, follow-up duration, outcome instruments, adverse events, withdrawals, and main clinical conclusions. The principal outcome measures considered in the synthesis were the Visual Analogue Scale (VAS), Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC), Knee injury and Osteoarthritis Outcome Score (KOOS), International Knee Documentation Committee score (IKDC), Lequesne index, SF-36, treatment satisfaction, and safety outcomes.
Methodological Quality and Risk-Of-Bias Assessment
The methodological quality of included studies was assessed according to study design. Randomized clinical trials were evaluated using the Cochrane Risk of Bias 2 tool, which considers bias arising from the randomization process, deviations from intended interventions, missing outcome data, measurement of outcomes, and selection of reported results. Non-randomized, retrospective, or quasi-experimental clinical studies were evaluated using ROBINS-I, which considers confounding, selection of participants, classification of interventions, deviations from intended interventions, missing data, measurement of outcomes, and selective reporting. Each study was classified as having low risk of bias, some concerns or moderate risk, or high/ serious risk of bias. The global judgment considered the adequacy of randomization, allocation concealment, blinding, baseline comparability, completeness of follow-up, use of validated outcome measures, transparency of reporting, and presence of clinically relevant confounding factors.
Quality Interpretation of The Selected Studies
The overall methodological quality of the 25 included studies was interpreted narratively because of heterogeneity in design, intervention protocols, PRP preparation, HA formulation, and follow-up duration. Randomized and double-blind trials with clearly described allocation procedures, balanced baseline characteristics, validated outcome instruments, and complete follow-up were considered higher-quality evidence. Open-label studies, retrospective designs, small samples, unclear allocation concealment, incomplete reporting of PRP composition, and limited control of confounding were considered factors that reduced methodological confidence. Studies with subjective outcomes, such as pain and function, were judged more critically when blinding was absent or insufficiently described.
Data Synthesis
Because relevant clinical heterogeneity was expected among the included studies, the primary synthesis was qualitative. Findings were organized according to comparator category: PRP combined with HA versus PRP alone, PRP combined with HA versus HA alone, PRP versus HA, and multi-arm injectable-comparator studies. For each category, the direction of effect, magnitude of clinical improvement, follow-up duration, adverse events, and consistency among studies were examined. Quantitative pooling was considered only if at least three studies were sufficiently homogeneous regarding population, intervention, comparator, outcome measure, and follow-up time. When meta-analysis was not appropriate, the results were summarized narratively based on clinical relevance and methodological quality.
Subgroup analyses were planned to explore potential sources of heterogeneity. The main subgroup variables included severity of osteoarthritis, PRP leukocyte content, number of injections, HA molecular weight, crosslinked versus non-crosslinked HA, simultaneous versus sequential PRP+HA administration, and follow-up duration. Follow-up was categorized as short term when outcomes were assessed up to 3 months, medium term at approximately 6 months, and long term at 12 months or more. Sensitivity analyses were planned by excluding studies with high risk of bias, retrospective studies, studies with incomplete PRP characterization, and studies with substantial missing outcome data.
Ethical Considerations
This systematic review was based exclusively on previously published clinical studies and did not involve direct contact with patients, collection of new individual data, or intervention in human participants. Therefore, institutional ethics approval and informed consent were not required for the review itself. When available, ethical approval and informed-consent procedures reported by the included studies were extracted as part of the methodological characterization.
Methods
Study Design and Reporting Framework
This systematic review was conducted to synthesize clinical evidence regarding the use of intra-articular platelet-rich plasma (PRP), either as an isolated intervention or in combination with hyaluronic acid (HA), for the treatment of knee osteoarthritis. The methodological structure followed the recommendations of the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 statement, with predefined procedures for formulation of the research question, identification of studies, eligibility assessment, data extraction, methodological quality appraisal, and qualitative synthesis of the evidence
Research Question and PICO Strategy
The review was guided by the following research question: in adult patients with knee osteoarthritis, does intra-articular PRP combined with HA provide superior clinical outcomes when compared with PRP alone or other injectable comparators? The population consisted of adults with clinical and/or radiographic diagnosis of knee osteoarthritis. The intervention of interest was intra-articular PRP associated with HA, administered either simultaneously or sequentially. The main comparator was PRP alone; however, studies including HA alone, corticosteroid, ozone, saline, placebo, or other injectable biologic therapies were also considered when they contributed clinically relevant comparative evidence. The outcomes of interest included pain, stiffness, physical function, patient-reported outcome measures, quality of life, treatment satisfaction, analgesic consumption, adverse events, and follow-up duration.
Information Sources
The literature search was performed in PubMed/MEDLINE, Scopus, Web of Science, Embase, Cochrane CENTRAL, PEDro, SciELO, and Google Scholar. Manual research was also performed in the reference lists of eligible studies to identify additional clinical articles that could meet the inclusion criteria. The search included studies published from January 2011 to May 2026. Only articles published in English and available as free full text were considered eligible for inclusion.
Search Strategy and Boolean Descriptors
The search strategy combined controlled vocabulary and free-text terms related to platelet-rich plasma, hyaluronic acid, and knee osteoarthritis. The main Boolean expression used was: (“platelet-rich plasma” OR PRP OR “plasma rich in growth factors” OR PRGF OR “autologous conditioned plasma”) AND (“hyaluronic acid” OR hyaluronan OR viscosupplementation OR “sodium hyaluronate”) AND (“knee osteoarthritis” OR “knee OA” OR gonarthrosis OR “degenerative knee disease”). To identify studies specifically evaluating combined therapy, the following expression was also applied: (“platelet-rich plasma” OR PRP) AND (“hyaluronic acid” OR HA OR hyaluronan) AND (combined OR combination OR concomitant OR sequential OR “one-week prior”) AND knee AND osteoarthritis. A clinical-study filter was added when supported by the database: (“clinical trial” OR randomized OR randomised OR “randomized controlled trial” OR “controlled trial” OR prospective OR retrospective OR experimental) AND (PRP OR “platelet-rich plasma”) AND (HA OR “hyaluronic acid”) AND knee. Outcome-oriented terms were also used to improve sensitivity, including WOMAC, KOOS, VAS, IKDC, Lequesne, pain, stiffness, function, and adverse events.
Eligibility Criteria
Studies were included when they met all predefined eligibility criteria. Eligible articles had to be clinical studies in humans, include adult participants diagnosed with knee osteoarthritis, evaluate intra-articular PRP, HA, PRP combined with HA, or another directly comparable injectable intervention, and report at least one clinical outcome related to pain, function, stiffness, quality of life, treatment response, or safety. Randomized clinical trials controlled clinical trials, prospective clinical studies, retrospective comparative clinical studies, and experimental clinical studies were accepted. Review articles, systematic reviews, meta-analyses, editorials, letters without original data, protocols without results, animal studies, in vitro investigations, surgical-only studies, non-English articles, inaccessible full texts, and studies without extractable clinical outcome data were excluded.
Study Selection
All retrieved records were exported to a reference-management system, and duplicate references were removed before the screening phase. Titles and abstracts were then independently assessed according to the predefined eligibility criteria. Studies considered potentially relevant were retrieved and evaluated in full text to confirm their inclusion. The selection process primarily prioritized clinical studies directly comparing platelet-rich plasma (PRP) alone with PRP combined with hyaluronic acid (HA). However, considering the limited number of direct comparative studies available, additional clinical investigations comparing PRP with HA or PRP+HA with HA were included as complementary evidence when they addressed the same clinical condition, used intra-articular administration, and reported comparable clinical outcomes.
The study selection process is summarized in Figure 1. Initially, 832 records were identified through database searching. After duplicate removal, 545 records remained for title and abstract screening. Of these, 419 records were excluded because they did not meet the eligibility criteria. Subsequently, 126 full-text articles were assessed for eligibility, and 101 articles were excluded for the following reasons: review or meta-analysis design, non-clinical study design, absence of a PRP/HA comparator, non-English language or unavailable free full text, duplicated population, or insufficient clinical data. After the complete screening and eligibility process, 25 clinical studies were included in the qualitative synthesis and quantitative synthesis considered when the data were sufficiently homogeneous.
Figure 1: PRISMA flow diagram of study selection
Data Extraction
Data was extracted using a standardized form developed for this review. The extracted variables included author, year of publication, country, study design, sample size, demographic characteristics, diagnostic criteria, Kellgren-Lawrence grade when available, intervention arms, comparator groups, PRP preparation method, leukocyte content when reported, HA formulation and molecular weight when available, number of injections, injection interval, use of imaging guidance, follow-up duration, outcome instruments, adverse events, withdrawals, and main clinical conclusions. The principal outcome measures considered in the synthesis were the Visual Analogue Scale (VAS), Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC), Knee injury and Osteoarthritis Outcome Score (KOOS), International Knee Documentation Committee score (IKDC), Lequesne index, SF-36, treatment satisfaction, and safety outcomes.
Methodological Quality and Risk-Of-Bias Assessment
The methodological quality of included studies was assessed according to study design. Randomized clinical trials were evaluated using the Cochrane Risk of Bias 2 tool, which considers bias arising from the randomization process, deviations from intended interventions, missing outcome data, measurement of outcomes, and selection of reported results. Non-randomized, retrospective, or quasi-experimental clinical studies were evaluated using ROBINS-I, which considers confounding, selection of participants, classification of interventions, deviations from intended interventions, missing data, measurement of outcomes, and selective reporting. Each study was classified as having low risk of bias, some concerns or moderate risk, or high/ serious risk of bias. The global judgment considered the adequacy of randomization, allocation concealment, blinding, baseline comparability, completeness of follow-up, use of validated outcome measures, transparency of reporting, and presence of clinically relevant confounding factors.
Quality Interpretation of The Selected Studies
The overall methodological quality of the 25 included studies was interpreted narratively because of heterogeneity in design, intervention protocols, PRP preparation, HA formulation, and follow-up duration. Randomized and double-blind trials with clearly described allocation procedures, balanced baseline characteristics, validated outcome instruments, and complete follow-up were considered higher-quality evidence. Open-label studies, retrospective designs, small samples, unclear allocation concealment, incomplete reporting of PRP composition, and limited control of confounding were considered factors that reduced methodological confidence. Studies with subjective outcomes, such as pain and function, were judged more critically when blinding was absent or insufficiently described.
Data Synthesis
Because relevant clinical heterogeneity was expected among the included studies, the primary synthesis was qualitative. Findings were organized according to comparator category: PRP combined with HA versus PRP alone, PRP combined with HA versus HA alone, PRP versus HA, and multi-arm injectable-comparator studies. For each category, the direction of effect, magnitude of clinical improvement, follow-up duration, adverse events, and consistency among studies were examined. Quantitative pooling was considered only if at least three studies were sufficiently homogeneous regarding population, intervention, comparator, outcome measure, and follow-up time. When meta-analysis was not appropriate, the results were summarized narratively based on clinical relevance and methodological quality.
Subgroup analyses were planned to explore potential sources of heterogeneity. The main subgroup variables included severity of osteoarthritis, PRP leukocyte content, number of injections, HA molecular weight, crosslinked versus non-crosslinked HA, simultaneous versus sequential PRP+HA administration, and follow-up duration. Follow-up was categorized as short term when outcomes were assessed up to 3 months, medium term at approximately 6 months, and long term at 12 months or more. Sensitivity analyses were planned by excluding studies with high risk of bias, retrospective studies, studies with incomplete PRP characterization, and studies with substantial missing outcome data.
Ethical Considerations
This systematic review was based exclusively on previously published clinical studies and did not involve direct contact with patients, collection of new individual data, or intervention in human participants. Therefore, institutional ethics approval and informed consent were not required for the review itself. When available, ethical approval and informed-consent procedures reported by the included studies were extracted as part of the methodological characterization.
Results
This systematic review included 25 clinical studies evaluating intra-articular injectable therapies for knee osteoarthritis, with emphasis on platelet-rich plasma (PRP), hyaluronic acid (HA), and the combined use of PRP+HA. The studies were analyzed according to the methodological strategy previously described, prioritizing direct comparisons between PRP alone and PRP associated with HA, while also incorporating complementary clinical evidence from studies comparing PRP with HA, PRP+HA with HA, and other injectable biological comparators. Overall, the included studies showed substantial heterogeneity in study design, sample size, osteoarthritis severity, PRP preparation, leukocyte concentration, HA molecular weight, number of injections, treatment interval, and follow-up duration. For this reason, the findings were synthesized qualitatively and organized into three tables: general characteristics of the studies, main clinical findings by comparator, and outcome-domain synthesis with methodological interpretation.
Table 1 summarizes the main characteristics of the 25 studies included in the review. Most studies evaluated patients with mild to moderate knee osteoarthritis, usually classified as Kellgren-Lawrence grades I to III. The most frequent outcomes were pain and function, assessed mainly by VAS, WOMAC, IKDC, KOOS, Lequesne index, and quality-of-life scales. Follow-up periods varied from short-term evaluations of 4 to 12 weeks to longer follow-up at 12 and 24 months.
|
Author/year |
Study design |
Comparison |
Follow-up |
Main outcomes |
|
Lana et al., 2016 |
Randomized, double-blind controlled trial |
HA vs PRP vs PRP+HA |
1, 3, 6, 12 months |
VAS, WOMAC |
|
Guo et al., 2016 |
Comparative clinical study |
PRP+HA vs PRP |
1, 3, 6, 12 months |
VAS, WOMAC, failures, adverse events |
|
Jacob et al., 2017 |
Comparative randomized study |
PRP vs PRP+LMW HA vs PRP+HMW HA |
6 weeks, 6 months |
VAS, IKDC |
|
Sun et al., 2021 |
Prospective randomized controlled trial |
Crosslinked HA+PRP vs PRP |
1, 3, 6 months |
VAS, WOMAC, Lequesne, SLS |
|
Wu et al., 2022 |
Prospective randomized double-blind trial |
PRP followed by HA vs PRP followed by saline |
1, 3, 6, 12 months |
WOMAC, balance, fall-risk parameters |
|
Branch et al., 2023 |
Randomized controlled trial |
PRP vs PRP+HA |
1, 3, 6, 12, 18, 24 months |
WOMAC, KOOS5, IKDC |
|
Palco et al., 2021 |
Retrospective comparative study |
PRP+HA vs leukocyte-rich PRP |
Short/medium term |
Clinical and functional outcomes |
|
Yu et al., 2018 |
Randomized clinical study |
PRP vs HA vs PRP+HA vs placebo |
Up to 12 months |
WOMAC, inflammatory markers |
|
Saturveithan et al., 2016 |
Retrospective clinical study |
HA+PRP vs HA |
6 months |
IKDC, VAS |
|
Riglet et al., 2026 |
Randomized multicenter non-inferiority trial |
PRP+non-crosslinked HA vs crosslinked HA |
1, 3, 6 months; extension to 12 months |
WOMAC, SF-36, responder criteria |
|
Filardo et al., 2012 |
Randomized double-blind prospective trial |
PRP vs HA |
2, 6, 12 months |
IKDC, EQ-VAS, Tegner, KOOS |
|
Raeissadat et al., 2015 |
Randomized clinical trial |
PRP vs HA |
12 months |
WOMAC, SF-36 |
|
Paterson et al., 2016 |
Double-blind randomized pilot trial |
Photo-activated PRP vs HA |
4 and 12 weeks |
VAS, KOOS, KQoL |
|
Tavassoli et al., 2019 |
Randomized controlled trial |
Single-dose PRP vs double-dose PRP vs HA |
4, 8, 12 weeks |
WOMAC, VAS |
|
Yaradilmis et al., 2020 |
Prospective randomized controlled study |
LR-PRP vs LP-PRP vs HA |
2, 6, 12 months |
VAS, WOMAC, recurrence |
|
Park et al., 2021 |
Randomized double-blind controlled trial |
Leukocyte-rich PRP vs HA |
6 weeks, 3 months, 6 months |
IKDC, VAS, WOMAC, PGA, growth factors |
|
Li et al., 2021 |
Retrospective comparative clinical study |
PRP vs HA |
1 and 6 months |
IKDC, WOMAC, VAS, cost, satisfaction |
|
Wang et al., 2022 |
Prospective double-blind randomized trial |
Single PRP vs crosslinked HA |
6 months |
WOMAC |
|
Ghorbani et al., 2024 |
Randomized clinical trial |
PRP vs HA |
Short term |
WOMAC pain, stiffness, function |
|
Szwedowski et al., 2022 |
Prospective randomized triple-parallel trial |
PRP vs HA vs corticosteroid |
6, 12, 26 weeks |
WOMAC |
|
Arliani et al., 2021/2022 |
Randomized clinical trial |
PRP vs HA |
6 months |
VAS, WOMAC, adverse events |
|
Jalali Jivan et al., 2021 |
Open-label clinical trial |
PRP vs HA |
1, 3, 6, 12 months |
VAS, KOOS, ROM |
|
Raeissadat et al., 2021 |
One-year randomized clinical trial |
PRP vs PRGF vs HA vs ozone |
2, 6, 12 months |
VAS, WOMAC, Lequesne |
|
Dulic et al., 2021 |
Prospective randomized clinical study |
BMAC vs PRP vs HA |
1, 3, 6, 9, 12 months |
VAS, WOMAC, KOOS, IKDC |
|
Barman et al., 2022 |
Single-blind randomized clinical trial |
IA-PRP vs IO+IA-PRP |
6 months |
VAS, KOOS, satisfaction |
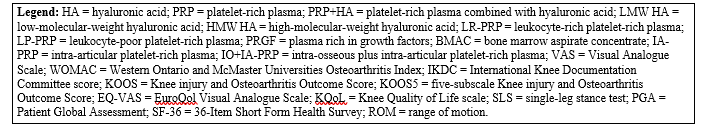
Table 1: General characteristics of the 25 included clinical studies
As shown in Table 1, the included studies varied considerably in design and intervention protocols. Several studies used randomized and blinded designs, strengthening the reliability of their findings, whereas others were retrospective or open-label, increasing the possibility of selection bias, performance bias, or confounding. The direct comparison between PRP+HA and PRP alone was available in a smaller number of studies, while comparisons between PRP and HA were more frequent. This distribution of evidence influenced the interpretation of the results, since conclusions regarding the superiority of PRP+HA over PRP alone were less robust than conclusions regarding PRP versus HA. Table 2 presents the main findings according to comparator category. The studies directly comparing PRP+HA with PRP alone showed inconsistent results. Lana et al. reported that PRP+HA produced early functional improvement compared with PRP alone, while Guo et al. observed improvement in both groups without statistically significant between-group differences. Jacob et al. found that PRP combined with low-molecular-weight HA produced the greatest numerical improvement in VAS and IKDC, although without statistical superiority. Branch et al. reported similar outcomes between PRP and PRP+HA up to 24 months.
|
Comparator category |
Studies |
Main findings |
Overall direction |
|
PRP+HA vs PRP alone |
1, 2, 3, 4, 5, 6, 7 |
Both interventions improved pain and function. Some studies showed early or medium-term benefit for PRP+HA, while others found no superiority over PRP. |
Inconsistent; PRP+HA not clearly superior to PRP |
|
PRP+HA vs HA alone |
1, 8, 9, 10 |
PRP+HA generally produced greater improvement than HA alone in pain, WOMAC domains, IKDC, or responder criteria. |
Favors PRP+HA over HA |
|
PRP vs HA |
11, 12, 13, 14, 15, 16, 17, 18, 19, 20, 21, 22 |
Most studies showed improvement in both groups. Several favored PRP, especially at 6-12 months; some showed equivalent outcomes. |
Frequently favors PRP, but not uniformly |
|
Multi-arm injectable comparator studies |
23, 24, 25 |
PRP or PRP-based strategies improved symptoms. PRGF, BMAC, or IO+IA-PRP showed favorable effects in selected studies. |
Supports biologic injectable approaches, with heterogeneity |
|
Legend: PRP = platelet-rich plasma; HA = hyaluronic acid; PRP+HA = platelet-rich plasma combined with hyaluronic acid; PRGF = plasma rich in growth factors; BMAC = bone marrow aspirate concentrate; IO+IA-PRP = intra-osseous plus intra-articular platelet-rich plasma; VAS = Visual Analogue Scale; WOMAC = Western Ontario and McMaster Universities Osteoarthritis Index; IKDC = International Knee Documentation Committee score; KOOS = Knee injury and Osteoarthritis Outcome Score; PASS = Patient Acceptable Symptom State. |
|||
Table 2: Summary of the main clinical findings according to comparator
Table 2 indicates that PRP-based interventions were consistently associated with clinical improvement, particularly in pain and function. When PRP was compared with HA, PRP more frequently showed superior outcomes, especially at medium- and long-term follow-up. Park et al. demonstrated that leukocyte-rich PRP produced significantly greater IKDC improvement than HA at 6 months and that higher growth-factor concentrations were associated with better clinical response. In contrast, Li et al. reported no significant inter-group differences between PRP and HA at 1 and 6 months, despite significant improvement in both groups, and emphasized the greater cost, longer preparation time, and higher frequency of post-injection pain and swelling associated with PRP.
The studies comparing PRP+HA with HA alone more consistently favored the combined intervention. Lana et al. found that PRP+HA improved pain and functional limitation compared with HA alone at 12 months. Yu et al. reported that combination therapy improved clinical and biological parameters more than isolated therapies in several outcomes. Riglet et al. also reported superiority of PRP+HA over crosslinked HA for WOMAC pain on walking and PASS WOMAC pain responder criteria at 6 months. Therefore, PRP+HA appeared more advantageous when the comparator was HA alone than when the comparator was PRP alone.
The outcome-domain synthesis is presented in Figure 2, which summarizes the qualitative strength of evidence across the main clinical domains evaluated in the included studies.
Pain, function, and safety received the highest qualitative score, indicating that these outcomes were consistently reported across most studies and showed a more robust pattern of clinical improvement after intra¬articular PRP, HA, or PRP+HA interventions. Pain and function were the most frequently assessed endpoints, mainly through VAS, WOMAC, IKDC, KOOS, and Lequesne scores, and they represented the core basis for comparing treatment efficacy among the included studies. Durability of response and overall quality of evidence showed favorable but less consistent results. Although several studies reported sustained clinical improvement, particularly after PRP-based interventions at medium- and long-term follow-up, the persistence of benefit varied according to PRP formulation, HA characteristics, injection protocol, and follow-up duration. The methodological quality of evidence was also considered favorable, but not uniformly strong, because the included studies differed in design, blinding, randomization, sample size, and reporting of PRP and HA preparation methods.
Stiffness received the lowest qualitative score among the evaluated domains. This does not indicate absence of clinical improvement but rather reflects that stiffness was less consistently reported and was often analyzed as a secondary component of broader instruments such as WOMAC. Therefore, the interpretation of stiffness outcomes was more limited when compared with pain and function.
Overall, Figure 2 demonstrates that the strongest and most consistent evidence among the 25 included studies was related to pain reduction, functional improvement, and safety. In contrast, durability, methodological certainty, and stiffness presented greater heterogeneity. These findings support the clinical relevance of PRP-based interventions for knee osteoarthritis while also highlighting the need for more standardized outcome reporting in future trials.

Figure 2: Qualitative strength of evidence across clinical outcome domains in studies evaluating PRP, HA, and PRP+HA for knee osteoarthritis
The methodological quality of the included studies is summarized in Figure 3. Overall, the evidence base was composed predominantly of studies with high or moderate methodological quality, although relevant variability was observed across the 25 clinical studies. Ten studies were classified as high quality, five as moderate-high quality, six as moderate quality, and four as lower quality.
The studies classified as high quality generally presented stronger methodological characteristics, including randomized design, controlled comparison groups, adequate follow-up, validated clinical outcome measures, and clearer reporting of intervention protocols. These studies provided the most reliable evidence for evaluating the clinical effects of PRP, HA, and PRP+HA in knee osteoarthritis.
The moderate-high and moderate quality categories included studies with relevant clinical contributions but with some methodological limitations, such as smaller sample size, shorter follow-up, limited blinding, incomplete reporting of PRP composition, or heterogeneity in HA formulation and injection protocols. Although these studies supported the overall synthesis, their findings required cautious interpretation because differences in study design and intervention characteristics could influence treatment effects.
The lower quality category included studies with greater risk of bias, mainly due to retrospective design, open-label allocation, limited control of confounding factors, or less detailed methodological reporting. These studies were retained in the qualitative synthesis because they addressed clinically relevant comparisons, but they were interpreted as complementary evidence rather than as the primary basis for conclusions.
Overall, Figure 3 demonstrates that the evidence supporting PRP-based interventions for knee osteoarthritis is methodologically heterogeneous. The presence of several high-quality clinical trials strengthens the review findings, particularly regarding pain, function, and safety outcomes. However, the inclusion of moderate and lower-quality studies highlights the need for cautious interpretation and reinforces the importance of future randomized, blinded, adequately powered trials with standardized PRP and HA preparation protocols.

Figure 3: Distribution of methodological quality among clinical studies evaluating intra-articular PRP, HA, and PRP+HA for knee osteoarthritis
Discussion
The findings of this systematic review indicate that intra-articular platelet-rich plasma (PRP), hyaluronic acid (HA), and PRP combined with HA are associated with symptomatic improvement in patients with knee osteoarthritis. However, the magnitude, duration, and consistency of these effects varied substantially among the included studies. This variability reflects important differences in study design, patient selection, osteoarthritis severity, PRP preparation, HA formulation, injection schedule, comparator group, and follow-up duration. Therefore, although the overall evidence supports the clinical usefulness of PRP-based therapies, the specific superiority of PRP+HA over PRP alone remains uncertain [1-25].
The strongest and most consistent finding across the studies included was improvement in pain and function after intra-articular treatment. Pain reduction was commonly assessed using VAS or WOMAC pain scores, while functional improvement was evaluated through WOMAC function, IKDC, KOOS, Lequesne index, and related patient-reported instruments. Most studies reported significant improvement from baseline, regardless of the injectable agent used. This suggests that PRP, HA, and PRP+HA may all provide symptomatic benefit in knee osteoarthritis. Nevertheless, comparative analysis showed that PRP-based interventions often produced more durable or clinically relevant improvement than HA alone, particularly at medium- and long¬term follow-up [11-24].
When PRP was compared with HA, several studies favored PRP, especially in outcomes related to pain, function, and global patient perception. Raeissadat et al. reported greater improvement with PRP than HA at one year, suggesting a more sustained clinical effect of PRP [12]. Tavassoli et al. showed that PRP, particularly a double-dose protocol, was superior to HA in improving WOMAC and VAS outcomes [14]. Yaradilmis et al. found that PRP formulations were more effective than HA in moderate gonarthrosis, although leukocyte-rich PRP was associated with more local post-injection reactions [15]. Park et al. demonstrated superior IKDC improvement with leukocyte-rich PRP compared with HA and linked clinical response to higher growth-factor concentrations, reinforcing the biological plausibility of PRP efficacy [16]. Similar superiority of PRP over HA was also observed in other clinical studies included in the review [19,20,22].
However, the advantage of PRP over HA was not universal. Some trials reported comparable outcomes between the two therapies. Filardo et al. found improvement in both groups without a clear overall superiority of PRP [11]. Paterson et al., in a pilot randomized trial, observed improvement after photo-activated PRP but did not demonstrate significant superiority over HA [13]. Li et al. reported similar clinical improvement after PRP and HA at 1 and 6 months, while also showing that PRP was associated with higher cost, longer treatment time, and more post-injection pain and swelling [17]. Wang et al. also found comparable improvement between single PRP injection and crosslinked HA in early knee osteoarthritis [18]. These findings are clinically important because they suggest that HA may remain a reasonable treatment option, particularly when crosslinked formulations are used, when cost is a concern, or when patients prefer a simpler and potentially better-tolerated intervention.
The evidence regarding PRP+HA was more complex. Studies comparing PRP+HA with HA alone tended to favor the combined intervention. Lana et al. reported that PRP+HA improved pain and functional limitation compared with HA alone, with benefits sustained up to 12 months [1]. Yu et al. observed favorable clinical and biological effects for PRP+HA compared with isolated therapies and placebo, suggesting a potential synergistic action between PRP and HA [8]. Saturveithan et al. found greater improvement with HA+PRP than HA alone in patients with more advanced knee osteoarthritis [9]. Riglet et al. also reported superiority of PRP+HA over crosslinked HA for selected WOMAC pain and responder outcomes [10]. Taken together, these findings suggest that adding PRP to HA may enhance the clinical effect of viscosupplementation.
In contrast, when PRP+HA was compared directly with PRP alone, the benefit of adding HA was inconsistent. Guo et al. found that both PRP+HA and PRP alone significantly improved pain and function, but without statistically significant between-group differences [2]. Jacob et al. reported numerical advantages for PRP combined with low-molecular-weight HA, although these differences were not statistically significant [3]. Sun et al. suggested a time-dependent effect, with PRP performing better at early follow-up and PRP+HA showing greater pain reduction later [4]. Wu et al. supported the potential benefit of a sequential protocol, in which PRP was administered before HA, suggesting that the timing of injections may affect therapeutic response [5]. However, Branch et al. found no long-term superiority of PRP+HA over PRP alone at 24 months [6]. Therefore, the current evidence suggests that PRP+HA may be superior to HA alone, but it cannot yet be considered consistently superior to PRP monotherapy.
This distinction is central to the interpretation of the review. If the clinical decision is between HA alone and PRP+HA, the combined intervention appears more favorable in several studies [1,8-10]. However, if the decision is between PRP alone and PRP+HA, the available evidence does not consistently justify the addition of HA [2-6]. This has practical relevance because PRP+HA may increase treatment costs, procedural complexity, and variability in preparation. Therefore, the indication for combined therapy should be individualized rather than assumed to be superior in all patients.
The possible biological rationale for PRP+HA is nevertheless compelling. HA may improve joint lubrication, restore viscoelastic properties of synovial fluid, reduce friction, and modulate nociceptive and inflammatory pathways. PRP, on the other hand, provides platelet-derived growth factors, cytokines, chemokines, and plasma proteins that may influence inflammation, chondrocyte metabolism, synoviocyte activity, and tissue repair mechanisms. Combining PRP and HA could theoretically provide complementary mechanical and biological effects. The clinical findings favoring PRP+HA over HA alone support this hypothesis [1,8-10]. However, the lack of consistent superiority over PRP alone suggests that the biological contribution of HA may be less relevant when PRP already provides a strong intra-articular biological stimulus.
One explanation for the inconsistent additive effect of HA is heterogeneity in PRP and HA preparations. PRP is not a standardized product. The included studies used different preparation systems, platelet concentrations, leukocyte contents, activation methods, and injected volumes. Leukocyte-rich PRP may produce stronger inflammatory reactions but may also contain higher concentrations of cytokines and growth factors, while leukocyte-poor PRP may be better tolerated. Yaradilmis et al. directly compared leukocyte-rich and leukocyte-poor PRP and found differences in both clinical response and local adverse effects [15]. Park et al. further demonstrated that PRP composition may influence clinical outcomes, as higher concentrations of growth factors were associated with better response [16]. These findings reinforce that PRP efficacy cannot be interpreted without considering its biological composition.
Similarly, HA formulations varied substantially. Molecular weight, crosslinking, concentration, source, and dosing schedule may influence residence time, mechanical properties, and clinical response. Jacob et al. compared PRP combined with low- and high-molecular-weight HA, suggesting that HA characteristics may affect outcomes [3]. Sun et al. used crosslinked HA in combination with PRP [4], whereas Riglet et al. compared PRP plus non-crosslinked HA with crosslinked HA alone [10]. Wang et al. showed that crosslinked HA may achieve clinical results like PRP in some patients [18]. These findings suggest that HA should not be treated as a single uniform comparator. The type of HA used may partly explain why some studies found a benefit of combination therapy while others did not.
Timing of administration may also be important. Some studies used simultaneous PRP+HA injection, whereas Wu et al. evaluated a sequential approach, administering PRP before HA [5]. This distinction may be biologically relevant. PRP may initially modulate the inflammatory environment and stimulate cellular responses, while HA administered later may support lubrication, reduce mechanical stress, and maintain a more favorable joint environment. If this sequential mechanism is correct, simultaneous injection may not reproduce the same biological effect. Future trials should therefore compare simultaneous and sequential PRP+HA protocols directly.
Diseases of severity is another important factor. Most studies included patients with mild to moderate knee osteoarthritis, but some enrolled in more advanced cases. PRP may be more effective in earlier diseases, when the joint environment still has sufficient biological responsiveness and structural damage is less severe. Filardo et al. suggested a possible trend favoring PRP in patients with lower-grade degeneration [11], and several trials involving mild to moderate disease showed favorable results for PRP [12,14-16,19,20,22]. In contrast, in advanced osteoarthritis, structural joint damage may limit the effect of biologic injections. However, Saturveithan et al. reported that HA+PRP improved symptoms even in grade III and IV disease [9], suggesting that combined therapy may still have a role in selected patients who are not candidates for immediate arthroplasty or who wish to delay surgery.
The studies with other injectable comparators provide additional context. Raeissadat et al. compared PRP, PRGF, HA, and ozone and found that PRP and PRGF had more durable effects than HA or ozone over one year [23]. This supports the concept that platelet-derived biologic therapies may offer longer-lasting benefits than non-biologic injectable options. Dulic et al. compared bone marrow aspirate concentrate, PRP, and HA, showing improvement in all groups but greater benefit with BMAC in some outcomes [24]. Barman et al. compared intra-articular PRP alone with combined intra-osseous and intra-articular PRP and found superior improvement with the combined approach [25]. These findings suggest that treatment response may depend not only on the injected product but also on the biological target, including intra¬articular tissues and subchondral bone.
Safety findings were generally favorable. Serious adverse events were rare across the included studies, and most reported complications were transient and self-limited. The most common adverse effects were local pain, swelling, stiffness, and discomfort after injection. PRP appeared to produce more frequent short-term inflammatory reactions than HA in some studies, particularly when leukocyte-rich preparations were used [15,17]. However, these reactions usually resolved without major intervention and did not outweigh the potential clinical benefits. Importantly, PRP+HA did not appear to substantially increase the risk of serious adverse events compared with PRP or HA alone [1,2,4,6,10]. This supports the general safety of PRP-based approaches when performed under appropriate sterile techniques and with adequate patient selection.
The methodological quality of the evidence should be interpreted carefully. The review included several randomized and blinded studies, which strengthen the reliability of the findings [1,4-6,10,11,13,16,18,20,23-25]. However, some studies were retrospective, open-label, small-sample, or had limited follow-up [2,3,7,9,17,21,22]. These limitations may introduce selection bias, performance bias, detection bias, or confounding. Furthermore, many studies did not fully describe PRP composition or HA characteristics, limiting reproducibility and comparability. This is particularly relevant because PRP and HA are biologically and mechanically heterogeneous interventions.
Another methodological limitation is the variability in outcome reporting. Although VAS and WOMAC were widely used, other instruments such as IKDC, KOOS, Lequesne, EQ-VAS, SF-36, and functional tests were reported inconsistently. This reduced the feasibility of quantitative pooling and supported the decision to perform a qualitative synthesis. Moreover, stiffness was less frequently reported as an independent outcome, which explains its lower strength of evidence in the outcome-domain synthesis. Future studies should adopt standardized core outcome sets for knee osteoarthritis injection trials, including pain, function, stiffness, patient global assessment, quality of life, adverse events, and treatment satisfaction.
The durability of response is particularly relevant for clinical decision-making. HA often provides short- to medium-term symptomatic relief, whereas PRP may provide longer-lasting improvement in several studies [12,14-16,19,20,22,23]. PRP+HA may offer early or medium-term benefit in some protocols [1,4,5,8-10], but long-term superiority over PRP alone was not consistently demonstrated [6]. Therefore, PRP appears to have stronger evidence for sustained benefit than HA, while the durability of PRP+HA as compared with PRP alone remains uncertain.
From a clinical perspective, the results suggest a treatment hierarchy that depends on the comparator. PRP seems more favorable than HA in many studies, especially for longer-term pain and function. PRP+HA seems more favorable than HA alone. However, PRP+HA does not consistently outperform PRP alone. Thus, in patients with mild to moderate knee osteoarthritis, PRP monotherapy may be considered an effective biologic option. PRP+HA may be considered when there is a rationale for combining viscosupplementation and biologic stimulation, but the additional cost and complexity should be balanced against the uncertain incremental benefit.
For patients, these findings should be communicated clearly. PRP and PRP+HA may reduce pain and improve function, but they are not curative treatments and should not be presented as cartilage-regenerating therapies without structural evidence. Most included studies focused on symptomatic outcomes rather than imaging-based disease modification. Therefore, the current evidence supports symptom control and functional improvement more strongly than structural regeneration. Future trials should include MRI outcomes, cartilage thickness, synovitis, bone marrow lesions, and progression to surgery to determine whether PRP-based therapies modify disease progression.
The results of this review indicate that PRP-based intra-articular therapy is clinically useful for knee osteoarthritis, especially in relation to pain relief and functional improvement. PRP is often superior to HA, but not in all studies. PRP+HA is generally superior to HA alone, but its superiority over PRP alone is inconsistent. These findings suggest that the combination of PRP and HA is promising, but its clinical role should be defined more precisely through standardized, adequately powered randomized trials. The future of this field depends on improved biological characterization of PRP, clearer classification of HA formulations, standardized injection protocols, longer follow-up, and better patient stratification.
Conclusion
This systematic review aimed to evaluate whether platelet-rich plasma alone or platelet-rich plasma combined with hyaluronic acid provides superior efficacy and safety in the treatment of knee osteoarthritis. Based on the 25 included clinical studies, PRP-based interventions demonstrated consistent clinical benefit, particularly for pain reduction and functional improvement, with a favorable safety profile. These effects were observed across studies evaluating PRP alone, PRP+HA, and comparative injectable therapies.
In response to the main objective, the evidence indicates that PRP+HA may provide greater clinical benefit than HA alone, especially in relation to pain, function, and responder outcomes. This finding supports the hypothesis that the combination of HA-mediated viscosupplementation with PRP-derived biological activity may be clinically useful in selected patients with knee osteoarthritis. However, when PRP+HA was compared directly with PRP alone, the results were heterogeneous and did not consistently demonstrate a statistically or clinically meaningful superiority of the combined treatment.
Therefore, PRP alone remains an effective therapeutic option for symptomatic knee osteoarthritis, particularly in patients with mild to moderate disease and when sustained improvement in pain and function is desired. PRP+HA should be considered a promising adjunctive strategy, especially when compared with HA alone, but the current evidence is insufficient to recommend it as universally superior to PRP monotherapy.
Regarding safety, PRP, HA, and PRP+HA were generally well tolerated. Serious adverse events were rare, and most reported complications were transient, including post-injection pain, swelling, stiffness, or local discomfort. PRP-based therapies may be associated with more short-term inflammatory symptoms than HA, particularly depending on leukocyte content, but these reactions were usually self-limited.
In conclusion, the available clinical evidence supports the use of PRP-based intra-articular therapy for knee osteoarthritis. The combination of PRP and HA appears biologically plausible and clinically promising, but its additional value over PRP alone remains uncertain. Future studies should use standardized PRP characterization, clearly defined HA formulations, homogeneous injection protocols, longer follow-up periods, and rigorous randomized controlled designs to determine which patients are most likely to benefit from combined PRP+HA treatment
References
- Lana, J. F., Weglein, A., Sampson, S. E., Vicente, E. F., Huber,S. C., Souza, C. V., ... & Belangero, W. D. (2016). Randomized controlled trial comparing hyaluronic acid, platelet-rich plasma and the combination of both in the treatment of mild and moderate osteoarthritis of the knee. Journal of stem cells & regenerative medicine, 12(2), 69.
- Guo, Y., Yu, H., Yuan, L., Yao, S., Yu, H., Wang, P., ... & Sun,S. (2016). Treatment of knee osteoarthritis with platelet-rich plasma plus hyaluronic acid in comparison with platelet-rich plasma only. Int J Clin Exp Med, 9(6), 12085-12090.
- Jacob, G., Shetty, V., & Shetty, S. (2017). A study assessing intra-articular PRP vs PRP with HMW HA vs PRP with LMW HA in early knee osteoarthritis. Journal of arthroscopy and joint surgery, 4(2), 65-71.
- Sun, S. F., Lin, G. C., Hsu, C. W., Lin, H. S., Liou, I. H. S., &Wu, S. Y. (2021). Comparing efficacy of intraarticular single crosslinked Hyaluronan (HYAJOINT Plus) and platelet-rich plasma (PRP) versus PRP alone for treating knee osteoarthritis. Scientific Reports, 11(1), 140.
- Gupta, A. (2022). Platelet-rich plasma one week prior to hyaluronic acid vs. platelet-rich plasma alone for the treatment of knee osteoarthritis. Biomedicines, 10(11), 2805.
- Branch EA, Urits I, Viswanath O, et al. (2023). Platelet-rich plasma versus platelet-rich plasma combined with hyaluronic acid for knee osteoarthritis: a two-year randomized clinical study. J Cartil Joint Preserv, 3, 100102.
- Palco, M., Fenga, D., Basile, G. C., Rizzo, P., Cavalieri, B., Leonetti, D., ... & Traina, F. (2021). Platelet-rich plasma combined with hyaluronic acid versus leucocyte and platelet-rich plasma in the conservative treatment of knee osteoarthritis. A retrospective study. Medicina, 57(3), 232.
- Yu, W., Xu, P., Huang, G., & Liu, L. I. N. (2018). Clinical therapy of hyaluronic acid combined with platelet-rich plasma for the treatment of knee osteoarthritis. Experimental and Therapeutic Medicine, 16(3), 2119-2125.
- Saturveithan, C., Premganesh, G., Fakhrizzaki, S., Mahathir, M., Karuna, K., Rauf, K., ... & Jaspreet, K. (2016). Intraarticular hyaluronic acid (HA) and platelet rich plasma (PRP) injection versus hyaluronic acid (HA) injection alone in patients with grade III and IV knee osteoarthritis (OA): a retrospective study on functional outcome. Malaysian orthopaedic journal, 10(2), 35.
- Riglet, L., Delgado, T., Lopez, R. F., Pers, Y. M., Cyteval, C., Adam, P., & Ornetti, P. (2026). Efficacy and safety of a combination of platelet-rich plasma with non-crosslinked hyaluronic acid versus a crosslinked hyaluronic acid, in single-injection for knee osteoarthritis. Randomized, controlled, multicenter, non-inferiority trial. BMC Musculoskeletal Disorders, 27(1), 272.
- Filardo, G., Kon, E., Di Martino,A., Di Matteo, B., Merli, M. L.,Cenacchi, A., ... & Marcacci, M. (2012). Platelet-rich plasma vs hyaluronic acid to treat knee degenerative pathology: study design and preliminary results of a randomized controlled trial. BMC musculoskeletal disorders, 13(1), 229.
- Raeissadat, S. A., Rayegani, S. M., Hassanabadi, H., Fathi, M., Ghorbani, E., Babaee, M., & Azma, K. (2015). Knee osteoarthritis injection choices: platelet-rich plasma (PRP) versus hyaluronic acid (a one-year randomized clinical trial). Clinical Medicine Insights: Arthritis and Musculoskeletal Disorders, 8, CMAMD-S17894.
- Paterson, K. L., Hunter, D. J., Metcalf, B. R., Eyles, J., Duong, V., Kazsa, J., ... & Bennell, K. L. (2018). Efficacy of intraarticular injections of platelet-rich plasma as a symptom-and disease-modifying treatment for knee osteoarthritis-the RESTORE trial protocol. BMC Musculoskeletal Disorders, 19(1), 272.
- Tavassoli, M., Janmohammadi, N., Hosseini, A., Khafri, S., & Esmaeilnejad-Ganji, S. M. (2019). Single-and double-dose of platelet-rich plasma versus hyaluronic acid for treatment of knee osteoarthritis: A randomized controlled trial. World journal of orthopedics, 10(9), 310.
- Yaradilmis, Y. U., Demirkale, I., Tagral, A. S., Okkaoglu,M. C., Ates, A., & Altay, M. (2020). Comparison of two platelet rich plasma formulations with viscosupplementation in treatment of moderate grade gonarthrosis: a prospective randomized controlled study. Journal of orthopaedics, 20, 240-246.
- Park, Y. B., Kim, J. H., Ha, C. W., & Lee, D. H. (2021). Clinicalefficacy of platelet-rich plasma injection and its association with growth factors in the treatment of mild to moderate knee osteoarthritis: a randomized double-blind controlled clinical trial as compared with hyaluronic acid. The American Journal of Sports Medicine, 49(2), 487-496.
- Sdeek, M., Sabry, D., El-Sdeek, H., & Darweash, A. (2021). Intra-articular injection of Platelet rich plasma versus Hyaluronic acid for moderate knee osteoarthritis. A prospective, double-blind randomized controlled trial on 189 patients with follow-up for three years. Acta Orthop Belg, 87(4), 729-734.
- Wang, Y. C., Lee, C. L., Chen, Y. J., Tien, Y. C., Lin, S.Y., Chen, C. H., ... & Huang, H. T. (2022). Comparing the efficacy of intra-articular single platelet-rich plasma (PRP)versus novel crosslinked hyaluronic acid for early-stage knee osteoarthritis: a prospective, double-blind, randomized controlled trial. Medicina, 58(8), 1028.
- Ghorbani A, et al. (2024). Platelet-rich plasma versus hyaluronic acid for symptomatic knee osteoarthritis: clinical outcomes after intra-articular injection. J Popul Ther Clin Pharmacol, 31:3270-3280.
- Szwedowski, D., Mobasheri, A., Moniuszko, A., ZabrzyÅ?ski, J., & Jeka, S. (2022). Intra-articular injection of platelet-rich plasma is more effective than hyaluronic acid or steroid injection in the treatment of mild to moderate knee osteoarthritis: a prospective, randomized, triple-parallel clinical trial. Biomedicines, 10(5), 991.
- Arliani, G. G., Durigon, T. S., Pedroso, J. P., Ferreira, G. F., Oksman, D., & Oliveira, V. O. (2022). Intra-articular infiltration of platelet-rich plasma versus hyaluronic acid in patients with primary knee osteoarthritis: preliminary results from a randomized clinical trial. Revista brasileira de ortopedia, 57(3), 402-408.
- Jivan, S. J., Monzavi, S. M., Zargaran, B., Alamdari, D. H., Afshari, J. T., Etemad-Rezaie, A., ... & Shariati-Sarabi, Z. (2021). Comparative analysis of the effectiveness of intraarticular injection of platelet-rich plasma versus hyaluronic acid for knee osteoarthritis: results of an open-label trial. Archives of Bone and Joint Surgery, 9(5), 487.
- Raeissadat, S. A., Ghazi Hosseini, P., Bahrami, M. H., Salman Roghani, R., Fathi, M., Gharooee Ahangar, A., & Darvish,M. (2021). The comparison effects of intra-articular injection of Platelet Rich Plasma (PRP), Plasma Rich in Growth Factor (PRGF), Hyaluronic Acid (HA), and ozone in knee osteoarthritis; a one year randomized clinical trial. BMC musculoskeletal disorders, 22(1), 134.
- Dulic, O., Rasovic, P., Lalic, I., Kecojevic, V., Gavrilovic, G., Abazovic, D., ... & Bumbasirevic, M. (2021). Bone marrow aspirate concentrate versus platelet rich plasma or hyaluronic acid for the treatment of knee osteoarthritis. Medicina, 57(11), 1193.
- Barman, A., Prakash, S., Sahoo, J., Mukherjee, S., Maiti, R., & Roy, S. S. (2022). Single intra-articular injection with or without intra-osseous injections of platelet-rich plasma in the treatment of osteoarthritis knee: a single-blind, randomized clinical trial. Injury, 53(3), 1247-1253.