

Advances in Bioengineering and Biomedical Science Research(ABBSR)
ISSN: 2640-4133 | DOI: 10.33140/ABBSR

Impact Factor: 1.7

Research Article - (2024) Volume 0, Issue 0
Using Viscoplastic Energy Model of GH-Method: Math-Physical Medicine to Investigate Relationships Between Diabetes Retinopathy and Hypoglycemia via TBR, Hyperglycemia via TAR (No. 1046, VMT #444)
Received Date: Mar 15, 2024 / Accepted Date: Apr 05, 2024 / Published Date: Apr 06, 2024
Copyright: ©©2024 Gerald C. Hsu. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.
Citation: Hsu, G. C. (2024). Using Viscoplastic Energy Model of GH-Method: Math-Physical Medicine to Investigate Relationships Between Diabetes Retinopathy and Hypoglycemia via TBR, Hyperglycemia via TAR (No. 1046, VMT #444). Adv Bioeng Biomed Sci Res, 7(2), 01-06.
Abstract
Diabetes mellitus is a metabolic disorder characterized by abnormal glucose metabolism, leading to conditions of hyperglycemia (high blood sugar) and, under certain conditions, hypoglycemia (low blood sugar). This relationship between diabetes and blood sugar level fluctuations is rooted in the disease's pathophysiology.
Hyperglycemia and Diabetes: In Type 2 diabetes, resistance to insulin—a hormone that regulates sugar movement into cells—or insufficient insulin production can lead to chronic hyperglycemia. Initially, the pancreas might produce extra insulin, but over time, it may not sustain the necessary levels. Untreated hyperglycemia can result in complications like cardiovascular disease, kidney damage (nephropathy), nerve damage (neuropathy), and retinal damage which leads into blindness (retinopathy).
Hypoglycemia and Diabetes: Despite hyperglycemia being a key characteristic of diabetes, those with the condition, particularly those undergoing insulin therapy or using certain glucose-lowering medications, risk developing hypoglycemia. This risk stems from imbalances among insulin levels, food intake, and physical activity. In Type 2 diabetes, hypoglycemia can occur when using insulin or certain medications that enhance insulin production, making the balance among medication, diet, and physical activity critical. Hypoglycemia can lead to confusion, seizures, and loss of consciousness, posing significant danger, such as sudden death.
The Balance: The pathophysiological link among diabetes, hyperglycemia, and hypoglycemia underscores the need for meticulous management, involving a mix of medication, diet, and physical activity to keep blood glucose levels within a target range and prevent both hyperglycemia and hypoglycemia. Continuous glucose monitoring (CGM) is vital for diet and exercise adjustments to avoid glucose level extremes.
The American Diabetes Association has announced guidelines for three metrics: time-in-range (TIR, between 70 mg/dL and 180 mg/dL), time-below-range (TBR, less than 70 mg/dL, indicating hypoglycemia), and time-above-range (TAR, higher than 180 mg/dL, indicating hyperglycemia).
This article draws on the author’s data collected from May 1, 2018, through March 19, 2024, and uses the Viscoplastic energy model (SD-VMT) to explore the relationship between diabetic retinopathy (DR) and glucose fluctuations, particularly hypoglycemia (TBR) and hyperglycemia (TAR).
Key Message
Both hypoglycemia (TBR) and hyperglycemia (TAR) significantly impact the occurrence of diabetic retinopathy. This fact is proven through applying engineering method of Viscoplastic energy model. Hypoglycemia TBR is typically associated with pancreatic beta cells dysfunction through lower fasting glucose levels, while hyperglycemia often correlates with excessive carbs/sugar consumption combined with inactivity.
Viscoelastic Medicine theory (VMT #444)
Using viscoplastic energy model of GH-Method: Math-Physical Medicine to investigate relationships between diabetes retinopathy and hypoglycemia via TBR, hyperglycemia via TAR (No. 1046)
Introduction
Diabetes mellitus is a metabolic disorder characterized by abnormal glucose metabolism, leading to conditions of hyperglycemia (high blood sugar) and, under certain conditions, hypoglycemia (low blood sugar). This relationship between diabetes and blood sugar level fluctuations is rooted in the disease's pathophysiology.Hyperglycemia and Diabetes
In Type 2 diabetes, resistance to insulin—a hormone that regulates sugar movement into cells—or insufficient insulin production can lead to chronic hyperglycemia. Initially, the pancreas might produce extra insulin, but over time, it may not sustain the necessary levels. Untreated hyperglycemia can result in complications like cardiovascular disease, kidney damage (nephropathy), nerve damage (neuropathy), and retinal damage which leads into blindness (retinopathy).
Hypoglycemia and Diabetes
Despite hyperglycemia being a key characteristic of diabetes, those with the condition, particularly those undergoing insulin therapy or using certain glucose-lowering medications, risk developing hypoglycemia. This risk stems from imbalances among insulin levels, food intake, and physical activity. In Type 2 diabetes, hypoglycemia can occur when using insulin or certain medications that enhance insulin production, making the balance among medication, diet, and physical activity critical. Hypoglycemia can lead to confusion, seizures, and loss of consciousness, posing significant danger, such as sudden death.
The Balance
The pathophysiological link among diabetes, hyperglycemia, and hypoglycemia underscores the need for meticulous management, involving a mix of medication, diet, and physical activity to keep blood glucose levels within a target range and prevent both hyperglycemia and hypoglycemia. Continuous glucose monitoring (CGM) is vital for diet and exercise adjustments to avoid glucose level extremes.
The American Diabetes Association has announced guidelines for three metrics: time-in-range (TIR, between 70 mg/dL and 180 mg/dL), time-below-range (TBR, less than 70 mg/dL, indicating hypoglycemia), and time-above-range (TAR, higher than 180 mg/dL, indicating hyperglycemia).
This article draws on the author’s data collected from May 1, 2018, through March 19, 2024, and uses the Viscoplastic energy model (SD-VMT) to explore the relationship between diabetic retinopathy (DR) and glucose fluctuations, particularly hypoglycemia (TBR) and hyperglycemia (TAR).
MPM Background
To learn more about his developed GH-Method: math-physical medicine (MPM) methodology, readers can read the following three papers selected from his published 760+ papers.
The first paper, No. 386 (Reference 1) describes his MPM methodology in a general conceptual format. The second paper, No. 387 (Reference 2) outlines the history of his personalized diabetes research, various application tools, and the differences between biochemical medicine (BCM) approach versus the MPM approach. The third paper, No. 397 (Reference 3) depicts a general flow diagram containing ~10 key MPM research methods and different tools.
The Authors Diabetes History
The author was a severe T2D patient since 1995. He weighed 220 lb. (100 kg) at that time. By 2010, he still weighed 198 lb. with an average daily glucose of 250 mg/dL (HbA1C at 10%). During that year, his triglycerides reached 1161 (high risk for CVD and stroke) and his albumin-creatinine ratio (ACR) at 116 (high risk for chronic kidney disease). He also suffered from five cardiac episodes within a decade. In 2010, three independent physicians warned him regarding the need for kidney dialysis treatment and the future high risk of dying from his severe diabetic complications.
In 2010, he decided to self-study endocrinology with an emphasis on diabetes and food nutrition. He spent the entire year of 2014 to develop a metabolism index (MI) mathematical model. During 2015 and 2016, he developed four mathematical prediction models related to diabetes conditions: weight, PPG, fasting plasma glucose (FPG), and HbA1C (A1C). Through using his developed mathematical metabolism index (MI) model and the other four glucose prediction tools, by the end of 2016, his weight was reduced from 220 lbs. (100 kg) to 176 lbs. (89 kg), waistline from 44 inches (112 cm) to 33 inches (84 cm), average finger-piercing glucose from 250 mg/dL to 120 mg/dL, and A1C from 10% to ~6.5%. One of his major accomplishments is that he no longer takes any diabetes-related medications since 12/8/2015
. In 2017, he achieved excellent results on all fronts, especially his glucose control. However, during the pre-COVID period, including both 2018 and 2019, he traveled to ~50 international cities to attend 65+ medical conferences and made ~120 oral presentations. This hectic schedule inflicted damage to his diabetes control caused by stress, dining out frequently, post-meal exercise disruption, and jet lag, along with the overall negative metabolic impact from the irregular life patterns; therefore, his glucose control was somewhat affected during the two-year traveling period of 2018-2019.
He started his COVID-19 self-quarantined life on 1/19/2020. By 10/16/2022, his weight was further reduced to ~164 lbs. (BMI 24.22) and his A1C was at 6.0% without any medication intervention or insulin injection. In fact, with the special COVID-19 quarantine lifestyle since early 2020, not only has he written and published ~500 new research articles in various medical and engineering journals, but he has also achieved his best health conditions for the past 27 years. These achievements have resulted from his non-traveling, low-stress, and regular daily life routines. Of course, his in-depth knowledge of chronic diseases, sufficient practical lifestyle management experiences, and his own developed high-tech tools have also contributed to his excellent health improvements.
On 5/5/2018, he applied a continuous glucose monitoring (CGM) sensor device on his upper arm and checks his glucose measurements every 5 minutes for a total of 288 times each day. Furthermore, he extracted the 5-minute intervals from every 15-minute interval for a total of 96 glucose data each day stored in his computer software. Through the author’s medical research work over 40,000 hours and read over 4,000 published medical papers online in the past 13 years, he discovered and became convinced that good life habits of not smoking, moderate or no alcohol intake, avoiding illicit drugs; along with eating the right food with well-balanced nutrition, persistent exercise, having a sufficient and good quality of sleep, reducing all kinds of unnecessary stress, maintaining a regular daily life routine contribute to the risk reduction of having many diseases, including CVD, stroke, kidney problems, micro blood vessels issues, peripheral nervous system problems, and even cancers and dementia. In addition, a long-term healthy lifestyle can even “repair” some damaged internal organs, with different required time-length depending on the particular organ’s cell lifespan. For example, he has “self-repaired” about 35% of his damaged pancreatic beta cells during the past 10 years.
Energy Theory
The human body and organs have around 37 trillion live cells which are composed of different organic cells that require energy infusion from glucose carried by red blood cells; and energy consumption from labor-work or exercise. When the residual energy (resulting from the plastic glucose scenario) is stored inside our bodies, it will cause different degrees of damage or influence to many of our internal organs.
According to physics, energies associated with the glucose waves are proportional to the square of the glucose amplitude. The residual energies from elevated glucoses are circulating inside the body via blood vessels which then impact all of the internal organs to cause different degrees of damage or influence, e.g. diabetic complications. Elevated glucose (hyperglycemia) causes damage to the structural integrity of blood vessels. When it combines with both hypertension (rupture of arteries) and hyperlipidemia (blockage of arteries), CVD or Stroke happens. Similarly, many other deadly diseases could result from these excessive energies which would finally shorten our lifespan. For an example, the combination of hyperglycemia and hypertension would cause micro-blood vessel’s leakage in kidney systems which is one of the major cause of CKD.
The author then applied Fast Fourier Transform (FFT) operations to convert the input wave from a time domain into a frequency domain. The y-axis amplitude values in the frequency domain indicate the proportional energy levels associated with each different frequency component of input occurrence. Both output symptom value (i.e. strain amplitude in the time domain) and output symptom fluctuation rate (i.e. the strain rate and strain frequency) are influencing the energy level (i.e. the Y-amplitude in the frequency domain).
Currently, many people live a sedentary lifestyle and lack sufficient exercise to burn off the energy influx which causes them to become overweight or obese. Being overweight and having obesity leads to a variety of chronic diseases, particularly diabetes. In addition, many types of processed food add unnecessary ingredients and harmful chemicals that are toxic to the bodies, which lead to the development of many other deadly diseases, such as cancers. For example, ~85% of worldwide diabetes patients are overweight, and ~75% of patients with cardiac illnesses or surgeries have diabetes conditions.
In engineering analysis, when the load is applied to the structure, it bends or twists, i.e. deform; however, when the load is removed, it will either be restored to its original shape (i.e, elastic case) or remain in a deformed shape (i.e. plastic case). In a biomedical system, the glucose level will increase after eating carbohydrates or sugar from food; therefore, the carbohydrates and sugar function as the energy supply. After having labor work or exercise, the glucose level will decrease. As a result, the exercise burns off the energy, which is similar to load removal in the engineering case. In the biomedical case, both processes of energy influx and energy dissipation take some time which is not as simple and quick as the structural load removal in the engineering case. Therefore, the age difference and 3 input behaviors are “dynamic” in nature, i.e. time-dependent. This time-dependent nature leads to a “viscoelastic or viscoplastic” situation. For the author’s case, it is “viscoplastic” since most of his biomarkers are continuously improved during the past 13-year time window.
Time-Dependent output Strain and Stress of (Viscous Input*Output Rate)
Hooke’s law of linear elasticity is expressed as:
Strain (ε: epsilon )
= Stress (σ: sigma) / Young’s modulus (E)
For biomedical glucose application, his developed linear elastic glucose theory (LEGT) is expressed as:
PPG (strain) = carbs/sugar (stress) * GH.p-Modulus (a positive number) + post-meal walking k-steps * GH.w-Modulus ( a negative number)
Where GH.p-Modulus is reciprocal of Young’s modulus E.
However, in viscoelasticity or viscoplasticity theory, the stress is expressed as:
Stress
= viscosity factor (η: eta) * strain rate (dε/dt)
Where strain is expressed as Greek epsilon or ε.
In this article, in order to construct an “ellipse-like” diagram in a stress-strain space domain (e.g. “hysteresis loop”) covering both the positive side and negative side of space, he has modified the definition of strain as follows:
Strain =
(body weight at certain specific time instant) He also calculates his strain rate using the following formula: Strain rate = (body weight at next time instant) - (body weight at present time instant)
He also calculates his strain rate using the following formula.
Strain rate =
(body weight at next time instant) - (body weight at present time instant)
The risk probability % of developing into CVD, CKD, Cancer is calculated based on his developed metabolism index model (MI) in 2014. His MI value is calculated using inputs of 4 chronic conditions, i.e. weight, glucose, blood pressure, and lipids; and 6 lifestyle details, i.e. diet, drinking water, exercise, sleep, stress, and daily routines. These 10 metabolism categories further contain ~500 elements with millions of input data collected and processed since 2010. For individual deadly disease risk probability %, his mathematical model contains certain specific weighting factors for simulating certain risk percentages associated with different deadly diseases, such as metabolic disorder-induced CVD, stroke, kidney failure, cancers, dementia; artery damage in heart and brain, micro-vessel damage in kidney, and immunity-related infectious diseases, such as COVID death.
Some of explored deadly diseases and longevity characteristics using the viscoplastic medicine theory (VMT) include stress relaxation, creep, hysteresis loop, and material stiffness, damping effect based on time-dependent stress and strain which are different from his previous research findings using linear elastic glucose theory (LEGT) and nonlinear plastic glucose theory (NPGT).
Results
Figure 1 shows Data table, TD and SD results.
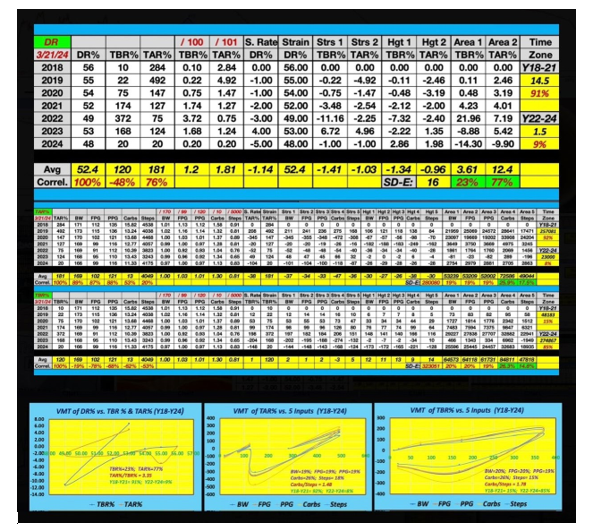
Figure 1: Data table, TD and SD results
Conclusions
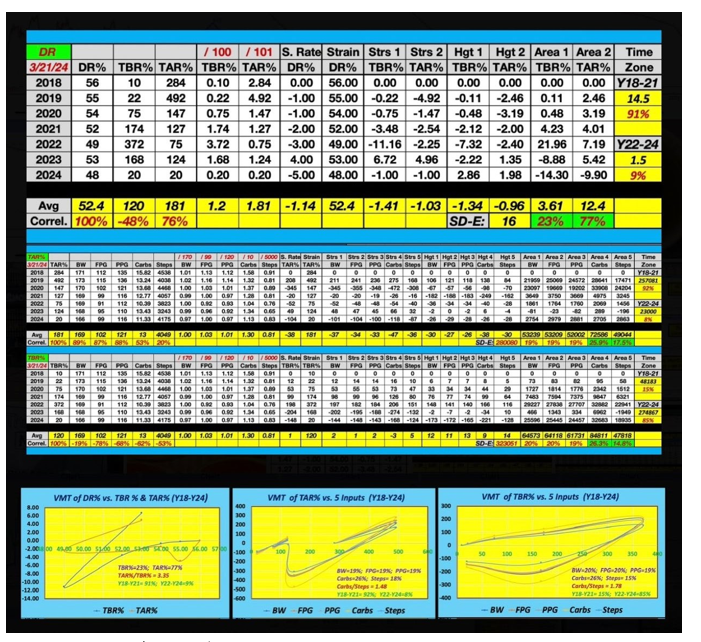
In summary, there are three key conclusions: First, his hyperglycemia via TAR contributes much more energy (77%) to his diabetic retinopathy (DR) than his hypoglycemia energy via TBR (23%), regardless his averaged TAR value is 1.8% and averaged TBR value is 1.2%.
Second, his SD-VMT analysis of hypoglycemia (TBR) against five inputs shows that body weight, fasting plasma glucose (FPG), and postprandial glucose (PPG) each contribute approximately 19% of the total energy. For hypoglycemia (TBR), the diet to exercise ratio is 1.48, with diet contributing 25.9% and exercise 17.5%.
Third, his SD-VMT analysis of hyperglycemia (TAR) against five identical inputs indicates that body weight, FPG, and PPG contribute nearly equal energy amounts (around 19% to 20% of the total energy). For hyperglycemia (TAR), the diet to exercise ratio for TAR is 1.78, with diet contributing 26.3% and exercise 14.8%.
In comparison, TAR contribution ratio of 1.78 is higher than TBR contribution ratio of 1.48 which has demonstrated the higher contribution of carbs/sugar consumption than exercise, particularly for the TAR case of hyperglycemia.
Fourth, the analysis of his time-zone energy distribution reveals the following insights: 91% of his energy related DR% versus TAR & TBR is concentrated between 2018 and 2021, with only 9% occurring from 2022 to 2024. This suggests a higher retinopathy risk during the earlier period.
92% of the energy associated with hyperglycemia TAR occurred between 2018 and 2021, with a mere 8% from 2022 to 2024. This indicates that the majority of his hyperglycemia-related energy in the earlier period can be attributed to higher postprandial glucose (PPG) levels due to increased carbohydrate and sugar intake.
Conversely, only 15% of the energy related to his hypoglycemia TBR was noted between 2018 and 2021, whereas a significant 85% has been observed from 2022 to 2024. This suggests that the majority of his hypoglycemia-related energy in the recent period is due to reduced body weight and fasting plasma glucose (FPG), reflecting improved health of pancreatic beta cells.
Key Message
Both hypoglycemia (TBR) and hyperglycemia (TAR) significantly impact the occurrence of diabetic retinopathy. This fact is proven through applying engineering method of Viscoplastic energy model. Hypoglycemia TBR is typically associated with pancreatic beta cells dysfunction through lower fasting glucose levels, while hyperglycemia often correlates with excessive carbs/sugar consumption combined with inactivity.
References
For editing purposes, majority of the references in this paper, which are self-references, have been removed for this article. Only references from other authors' published sources remain. The bibliography of the author’s original self-references can be viewed at www.eclairemd.com.
Readers may use this article as long as the work is properly cited, and their use is educational and not for profit, and the author’s original work is not altered.
For reading more of the author’s published VGT or FD analysis results on medical applications, please locate them through platforms for scientific research publications, such as ResearchGate, Google Scholar, etc.