

Advances in Bioengineering and Biomedical Science Research(ABBSR)
ISSN: 2640-4133 | DOI: 10.33140/ABBSR

Impact Factor: 1.7

Case Report - (2022) Volume 5, Issue 1
A New Surgical Attempt for Severe Hepatic Trauma: A Case Report
2Department of Hepatopancreatobiliary Surgery, Taizhou people’s Hospital, Taizhou, Jiangsu 225300, China
Received Date: Dec 23, 2021 / Accepted Date: Dec 27, 2021 / Published Date: Jan 10, 2022
Copyright: ©Copyright: ©2022 Chang-He Zhang. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.
Citation: Guang-Ning Su, Chang-He Zhang. (2022). A New Surgical Attempt for Severe Hepatic Trauma: A Case Report. Adv Bioeng Biomed Sci Res 5(1):01-03.
Abstract
Liver injury is common in abdominal injuries and its prognosis is closely related to the grade and management of the injury. Although the range of non-surgical treatment (NOM) is becoming wider and wider, surgical treatment is still an irreplaceable treatment for some patients with severe liver injury. We encountered a patient with a grade �?� liver laceration. Because of the particularity of the injury site and the desire to avoid a second operation, we adopted a new surgical method. We ligated the initial segment of the main bleeding vessel, left the drainage tube in the rupture, and finally closed the hepatic surface rupture. This relatively simple operation eventually cured the patient. So far, the results have been satisfactory. We report a case of a young male with grade �?� liver injury after a traffic accident. Due to the severity of the injury, hemodynamic instability, and the presence of peritonitis, we used a new and simple surgical approach to treat the patient, and the patient recovered successfully without additional surgery or serious complications. This may give doctors new ideas for dealing with similar injuries to the liver.
Keywords
Blunt liver Injury; Trauma; Surgical Treatment; Non-Operative Management
Case Report
In December 2018, a 26-year-old man was sent to our hospital with severe abdominal pain after a traffic accident. On admis-sion, his systolic blood pressure was less than 90mmHg and his heart rate exceeded 120 beats per minute. Physical examina¬tion showed a sign of local peritoneal irritation. The dynamic CT scan showed that the lesions involved liver segments â?£, â?¤ and â?§, and there was obvious contrast medium exudation in the right anterior hepatic pedicle (Fig. 1A). In addition, pneu-mothorax, right renal contusion and colonic contusion can also be seen. The operation began immediately after the establish¬ment of an intravenous infusion channel and the placement of a thoracic drainage device. On entering the abdomen, we found that blood continued to gush from the fissure on the surface of the liver on the right side of the falciform ligament. The shape of the liver fissure is similar to the trapezoid in the geometric shape, the depth of the fissure is about 12cm, and the bottom is obviously wider than the opening. We first compressed the fissure to control the rate of bleeding and then dissected the first porta hepatis. After blocking hepatic blood flow by Pringle ma¬neuver, we found that the damaged blood vessels and bile ducts in the fissure were still difficult to repair unless more normal liver tissue was cut open to enlarge the fissure. So, we took a different approach. First of all, in order to stop the bleeding ade¬quately, the right hepatic artery and the right anterior portal vein were ligated successively. Secondly, after choledochectomy was placed through the common bile duct to explore the integrity of the anterior and posterior branches of the right hepatic duct, the T-tube was retained to drain bile. Two fissure drainage tubes were then placed through the right posterior lobe of the liver and the gallbladder bed, respectively. Finally, the fissure on the surface of the liver was sutured carefully, and the round ligament of the liver was covered and fixed on the fissure. We repaired the serosa of the colon during the operation. After seeking the guid¬ance of a urologist, we adopted conservative treatment for renal subcapsular hematoma. After symptomatic treatment, the liver function indexes gradually returned to normal and the patient was discharged from hospital. One month after the operation, CT showed that the fissure was significantly reduced, the drain¬age tube in the fissure was in place, and there was no intrahepatic infection or bleeding (Figure 1B). Thereafter, the intrahepatic drainage volume gradually disappeared. CT at 3 months after surgery showed further narrowing of the liver fissure and no oth¬er abnormalities (Fig. 1C). At this time, the T tube and drainage were pulled out after continuous clamping. Follow-up for 2 years showed that the patient recovered well with no complications.
Discussion
The incidence of blunt liver trauma has increased gradually in the past 30 years, and has become the leading cause of death of severe abdominal trauma[1, 2]. With advances in treatment of trauma and interventional radiology, non-operative manage¬ment (NOM) is now the standard of care for blunt liver trauma, provided that the hemodynamics are stable. The success rate of NOM is around 90% [3]. However, studies have pointed out that up to 35% of patients with severe liver injury need emergency surgery [4]. International guidelines agree that patient with he¬modynamic instability or peritonitis should undergo an explor¬atory laparotomy immediately [5]. Immediate control of liver bleeding is the primary task of emergency surgery. This is the following conditions for definitive surgery such as liver repair and liver resection [4]. Severe liver trauma with extensive paren-chymal injury and uncontrollable bleeding can rapidly develop into a lethal triad, including coagulopathy, severe acidosis and hypothermia. Correcting these problems can be very challenging for trauma surgeons [6]. Performing complex and lasting sur¬gery is like opening Pandora’s box, which can lead to a serious waste of time, failure to significantly improve overall survival, and may expose patients to significantly higher life threats [6, 7]. Under this circumstance, the concept of damage control surgery (DCS) came into being and developed. The principles of DCS include primary control of bleeding and contamination, and sec¬ondary surgery after physiological resuscitation. This approach has been shown to improve survival in patients with critical inju¬ries and shock, but it can also lead to excessive consumption of medical resources, increased complications, and prolonged ICU and hospital stays [8]. If the bleeding is limited to a branch of the hepatic artery or portal vein, ligation of the criminal vessel is the first choice. However, the bleeding in our patient stopped only after the right hepatic artery and the right anterior branch of the portal vein were ligated at the same time. This method of controlling bleeding from liver trauma is rare. According to some reports, when the blood flow into the liver is interrupted by embolization or ligation, the necrotic liver tissue with loss of blood supply needs to be resected or debrided repeatedly [9]. However, in the end, we did not have additional surgery. From the follow-up review, we can see that although necrosis occurred in the middle of the damaged liver tissue, there was no serious infection, which may benefit from the adequate drainage of ne¬crotic tissue in the liver fissure and the effective control of bile leakage. Compensatory hyperplasia occurs in the marginal part, which may benefit from the collateral circulation of blood flow from the surrounding normal liver tissue. Although some studies have described the non-operative treatment of isolated hepatic necrosis in patients with hepatic trauma after hepatic artery em¬bolization, the conservative treatment of hepatic necrosis after ligation of hepatic artery and portal vein branches during oper¬ation has not been reported[10]. In addition, different from the traditional methods of opening liver fissures and fully repairing them, we use the method of sealing liver surface fissures. This effectively isolates the contamination of the abdominal cavity by the necrotic tissue in the liver. The round hepatic ligament with rich blood supply is fixed on the repaired liver wound, which is beneficial to the closure and healing of liver fissure. The repair one by one of the damaged vessels in the fissure is avoided by li-gating the root of the bleeding vessels within the first portal. The drainage of common bile duct effectively reduces the pressure of intrahepatic bile duct and is beneficial to the healing of intrahe¬patic bile leakage. We report a new experience in the treatment of severe liver trauma, that is, ligation of the root of bleeding blood vessels at the first porta, closure of the hepatic fissure, and adequate drainage in the fissure. Finally, the injury of normal liver tissue, extensive hepatectomy and secondary operation, as well as liver abscess, intra-abdominal bleeding and other com¬plications were avoided. The patient recovered. This relatively simple surgical method can provide surgeons with new options in the face of patients with similar severe liver trauma.
Acknowledgements: none
Conflict of interest: none

Figure 1A: preoperative dynamic CT scan showed a grade liver laceration, mainly located in liver segments
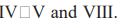 . Obvious contrast medium exudation in the right anterior hepatic pedicle.
Figure 1B: one month after the operation, dynamic CT showed postoperative changes, the extent of the liver lesion was smaller than before. Slight hyperplasia occurred in the liver tissue surrounding the lesion. Drainage tube could be seen in the closed fissure and slight effusion was seen around the liver.
Figure 1C: 3 months after operation, dynamic CT showed that the liver lesions were further reduced, and a small amount of old hemorrhage could be seen in the liver. The liver tissue surrounding the lesion was further proliferated. There was no obvious effusion in the abdominal cavity.
References
- Virdis F, Reccia I, Di Saverio S, G Tugnoli, S H Kwan, et al. (2019) Clinical outcomes of primary arterial embolization in severe hepatic trauma: A systematic review. Diagn Interv Imaging 100: 65-75.
- Melloul E, Denys A, Demartines N (2015) Management of severe blunt hepatic injury in the era of computed tomography and transarterial embolization: A systematic review and critical appraisal of the literature. J Trauma Acute Care Surg 79: 468-474.
- Anand RJ, Ferrada PA, Darwin PE, Bochicchio GV, Scalea TM (2011) Endoscopic retrograde cholangiopancreatography is an effective treatment for bile leak after severe liver trauma. J Trauma 71: 480-485.
- Ward J, Alarcon L, Peitzman AB (2015) Management of blunt liver injury: what is new? Eur J Trauma Emerg Surg 41: 229-237.
- Ruscelli P, Gemini A, Rimini M, Sergio Santella, Roberto Candelari, et al. (2019) The role of grade of injury in non-operative management of blunt hepatic and splenictrauma: Case series from a multicenter experience. Medicine (Baltimore) 98: 16746.
- Tarchouli M, Elabsi M, Njoumi N, Essarghini M, Echarrab M, et al. (2018) Liver trauma: What current management? Hepatobiliary Pancreat Dis Int 17: 39-44.
- Liu PP, Chen CL, Cheng YF, Pei Min Hsieh, Bool Lee Tan, et al. (2005) Use of a refined operative strategy in combination with the multidisciplinary approach to manage blunt juxtahepatic venous injuries. J Trauma. 59: 940-945.
- Benz D, Balogh ZJ (2017) Damage control surgery: current state and future directions. Curr Opin Crit Care 23: 491-497.
- Tanaka H, Honna T, Muto M, Akihiro Fujino, Mureo Ka-sahara, et al. (2011) Selective ligation of portal vein and hepatic artery for ruptured hepatocellular carcinoma in a 13-year-old boy. J Pediatr Surg 46: 973-7.
- Abdelrahman H, Ajaj A, Atique S, El Menyar A, Al Thani H (2013) Conservative management of major liver necrosis after angioembolization in a patient with blunt trauma. Case Rep Surg 2013: 954050.